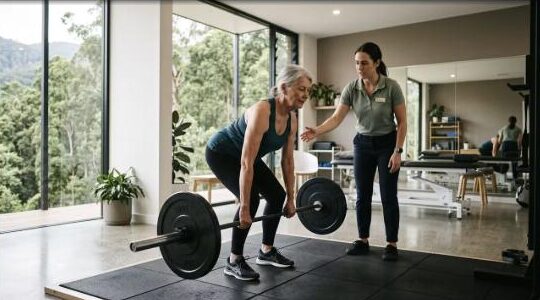A 68-year-old walks into a clinic. They have been told, at some point in the last decade, that their knee is “bone on bone.”
They have stopped bushwalking. They have stopped the stairs. They have stopped the golf. Not because the knee hurt too much to do those things — but because they were given a mental image of two bare bones grinding together, and every step now feels like it is spending something they cannot get back.
Those four words have taken more walking out of the world than the underlying condition ever did.
The uncomfortable truth about knee imaging
Knee osteoarthritis goes by many names: knee arthritis, degenerative joint disease, wear and tear arthritis, degenerative knee, gonarthrosis, knee OA, and — colloquially — bone on bone.
Here is what the research consistently shows: the relationship between what a knee X-ray looks like and how much a knee hurts is surprisingly weak.
Plenty of people have severe radiographic changes and minimal pain. Plenty have near-normal X-rays and significant pain. Systematic reviews of this discordance have been published repeatedly since the 1990s and the finding is robust.
Which means the X-ray is a description of a joint’s appearance, not a prognosis for a person’s life.
What actually predicts how a knee behaves
Three things, none of which appear on the radiology report:
Quadriceps strength. This is the big one. Quadriceps weakness is both a consequence and a cause of knee osteoarthritis. A strong quadriceps distributes load across the joint, controls the tibia, and absorbs the impact that would otherwise go through cartilage. Weak quads mean every step lands harder.
Load tolerance. Cartilage and bone are living tissue. They adapt to load. The idea that a joint has a fixed number of steps in it, like a car odometer, is a mechanical metaphor applied to biology, and biology does not work that way. Astronauts do not come back from space with better cartilage.
Beliefs and behaviour. People who believe their joint is being destroyed by walking stop walking. Then their quads weaken, their weight rises, their aerobic fitness falls, their pain worsens, and the belief appears confirmed.
What the evidence says about exercise
The GLA:D program — Good Life with osteoArthritis in Denmark — is now run across Australia, including in Queensland. It combines education with supervised progressive exercise for knee and hip osteoarthritis. Across large registry datasets, participants report meaningful reductions in pain and improvements in function, and a substantial proportion of people who were considering joint replacement change their mind.
This is not fringe. Australian and international clinical guidelines list exercise and education as first-line treatment for knee osteoarthritis, ahead of injections and well ahead of surgery.
The longevity angle nobody mentions
Here is why this article sits on a longevity clinic’s website.
A painful knee is not primarily a knee problem. It is a dose of activity problem. When a 66-year-old stops walking because of knee arthritis:
- Their VO2 max declines, and cardiorespiratory fitness is one of the strongest mortality predictors in existence
- Their muscle mass declines across the whole body, not just the leg
- Their bone density declines from reduced loading
- Their balance declines, raising fall risk
- Their metabolic health worsens
- Their social contact typically shrinks
The knee did not shorten their life. The response to the knee did.
This is why the goal of knee osteoarthritis management at Longevity Physio Studio is never simply “less pain.” It is “more capacity” — because capacity is what buys years.
What we actually do
At our Eagle Heights clinic on Tamborine Mountain, a knee osteoarthritis assessment includes quadriceps and hamstring strength testing, 30-second sit-to-stand, gait analysis, knee range of motion, hip and ankle screening (a stiff ankle or weak hip loads a knee badly), and a frank conversation about what the imaging does and does not mean.
Then we load it. Progressively, at an intensity that produces adaptation. Leg press, step-ups, split squats, sit-to-stand progressions, and eventually loaded patterns that most people with knee arthritis have been told to avoid for twenty years.
Some soreness during and after loading is normal and is not damage. We use a simple pain-monitoring framework so you can tell the difference between the two.
When surgery is the right answer
Sometimes it is. If pain is unrelenting at night, function is severely limited despite genuine strength work, and quality of life is significantly compromised, a knee replacement is an excellent operation.
But the strongest predictor of how well you do after a knee replacement is how strong you were before it. Even if you are heading for surgery, the strength work is not wasted — it is the single best investment in your outcome.
Book a knee assessment
If you have been told your knee is bone on bone, degenerative, or worn out, get a second opinion about what that actually means for you.
Longevity Physio Studio is in Eagle Heights, Mt Tamborine, serving Tamborine Mountain, North Tamborine, Canungra and the Gold Coast hinterland. Book an assessment.