Someone with a stubborn tendon problem eventually arrives at a decision point. They have tried rest, they have tried anti-inflammatories, and they are now being offered something that costs several hundred dollars and involves a needle.
There are two very different needle-based options in circulation, and the reasoning behind them is worth understanding before you spend the money.
What PRP is
Platelet-rich plasma involves drawing your blood, centrifuging it to concentrate the platelets, and injecting that concentrate into the injured tissue.
The rationale is sound in principle. Platelets contain growth factors — PDGF, TGF-beta, VEGF, IGF-1 — which are genuinely involved in tissue repair. Concentrating them at the site of a degenerative tendon should, in theory, stimulate healing.
The theory is elegant. The trial results have been more complicated.
What the trials have found
The most instructive finding comes from studies that included a proper placebo — a saline injection performed identically.
The RESTORE trial, published in JAMA in 2021, examined PRP for Achilles tendinopathy against a placebo injection. It found no significant difference in outcomes at six months.
Trials of PRP for plantar fasciitis have similarly found limited advantage over placebo in well-controlled studies.
For knee osteoarthritis, the evidence is mixed, with some positive trials and some well-conducted placebo-controlled trials showing no meaningful difference.
For lateral elbow tendinopathy, results have been variable.
The pattern across the literature: PRP tends to perform reasonably well against no treatment or against corticosteroid, and considerably less well when the comparison is a properly blinded placebo injection.
There is also enormous heterogeneity in what “PRP” actually means — platelet concentration, leukocyte content, activation method and injection protocol all vary widely between studies and between clinics. Some of the inconsistency in results may reflect this. The field is still working out what the optimal preparation is.
What dry needling is
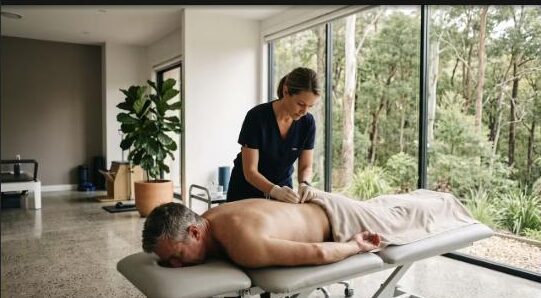
Dry needling uses a thin filiform needle inserted into a taut band of muscle to elicit a local twitch response. Nothing is injected — hence “dry.”
Its mechanisms are described in detail elsewhere on this site: mechanical disruption of the contracted region, reduction in abnormal motor endplate activity, changes in the local biochemical environment, improved local blood flow, a controlled inflammatory and healing response, and segmental and descending pain modulation.
Where the evidence sits
The evidence for dry needling is best described as moderate quality, showing meaningful short-term improvements in pain and range of motion for myofascial pain across a range of body regions. The long-term evidence for dry needling as a standalone treatment is weaker.
That is an honest summary, and it is not a claim of superiority. Dry needling and PRP are studied in overlapping but not identical conditions, and no one should present a head-to-head verdict that the literature does not support.
The genuinely useful comparison
Rather than “which is better,” here are the practical differences that actually matter to a decision.
Cost. Dry needling is typically delivered within a standard physiotherapy consultation. PRP is a separate procedure with a separate fee, commonly in the hundreds of dollars per injection, often not rebated, and frequently recommended as a series.
What they target. Dry needling addresses muscle — taut bands, trigger points, and the referred pain they produce. PRP targets tendon, ligament or joint tissue. If the source of your pain is muscular, PRP is aimed at the wrong tissue. If your problem is a genuinely degenerative tendon, needling a muscle will not resolve it. Accurate diagnosis determines which question you are even asking.
Reversibility and risk. Both are low-risk in trained hands. Dry needling carries minor bruising and post-treatment soreness, with rare serious events tied to anatomical region. PRP involves a blood draw and an injection into deeper tissue.
Recovery protocol. PRP typically requires a period of relative rest afterwards, which — for a condition where loading is the primary treatment — is a real cost that is rarely factored in.
The point both approaches share
Here is the thing that gets lost in the comparison entirely.
Tendinopathy is fundamentally a capacity problem. The tendon is being asked to do more than it can currently tolerate. The single intervention with the strongest evidence base for tendinopathy — stronger than any injection — is progressive loading: heavy slow resistance training, appropriately dosed, over months.
Neither dry needling nor PRP builds capacity. Both are, at best, ways to reduce pain enough that you can do the loading work that actually changes the tendon.
A patient who has PRP and then does nothing has bought an expensive pause. A patient who has dry needling and then does nothing has bought a cheap one.
The variable that determines the outcome is the twelve weeks of progressive loading that follows.
Our approach
At Longevity Physio Studio in Eagle Heights, Mt Tamborine, the first step is always establishing what tissue is actually generating your symptoms — muscle, tendon, joint, or nerve — because that determines everything downstream.
We use dry needling where the presentation suggests it will help. We build a loading program regardless. And where an injection is a reasonable option worth discussing with your GP or sports physician, we will say so — it is your decision to make with the relevant information in front of you.
This article is general information, not personal medical advice.
Book an assessment
If you have a stubborn tendon or muscle problem and you are weighing up an injection, it is worth getting a clear diagnosis first.
Longevity Physio Studio, Eagle Heights, Mt Tamborine — serving Tamborine Mountain, North Tamborine, Canungra and the Gold Coast hinterland. Book an assessment.