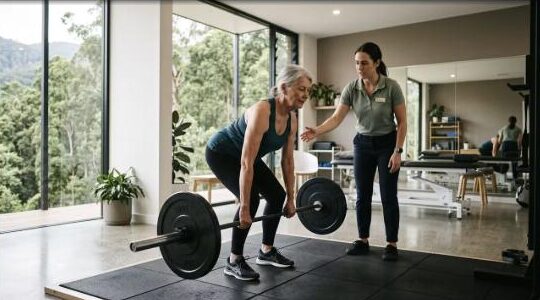The GLP-1 receptor agonist medications have changed obesity treatment. The weight loss they produce is substantial, sustained while treatment continues, and comes with genuine cardiovascular and metabolic benefits demonstrated in large trials.
This article is not an argument against them. That is a decision for you and your doctor.
It is about a specific problem that is under-discussed, and about what you can do about it — because the window to act is while you are losing the weight, not afterwards.
The finding
Body composition substudies from the major trials used DXA scanning to separate fat loss from lean mass loss.
In the STEP 1 substudy of semaglutide, participants lost substantial total body weight. Approximately 39% of that weight loss was lean body mass.
The SURMOUNT-1 substudy of tirzepatide reported a broadly comparable pattern, with roughly a quarter to a third of weight lost coming from lean mass.
The context that matters
Here is where accuracy is important, because this finding gets sensationalised in both directions.
Some lean mass loss occurs with any weight loss. Whether you lose weight through diet, surgery, or medication, a portion of the loss is lean tissue. This is normal physiology — as fat mass falls, the body needs less structural and metabolic tissue to carry it, and some lean loss is appropriate. “Lean mass” on DXA also includes water, glycogen, connective tissue and organ mass, not just contractile muscle.
The proportions in the GLP-1 trials are broadly in line with what is seen in other rapid weight loss interventions. These medications are not uniquely destructive to muscle.
But the absolute quantity is large, because the total weight loss is large. Losing 39% of lean mass from a 15 kg loss is a very different amount of tissue from losing 39% of a 4 kg loss.
And critically: in the trials, participants were generally not doing structured resistance training. That is the modifiable variable.
Why this matters more after 55
For a 32-year-old losing 20 kg, some lean mass loss is manageable and largely recoverable.
For a 64-year-old, the calculation is different:
- Age-related sarcopenia is already underway. Adding accelerated lean mass loss on top compounds an existing decline.
- Muscle is the primary site of glucose disposal. Losing it works against the metabolic goal of the treatment.
- Bone density falls with weight loss too. Reduced mechanical loading plus reduced lean mass is a meaningful bone risk, and some GLP-1 studies have reported bone mineral density reductions.
- Regain is compositionally uneven. If treatment stops and weight returns, the evidence from weight-cycling research suggests fat regains preferentially over muscle — leaving a person at their original weight with a worse body composition than before.
- Strength is what independence is made of. Grip strength, sit-to-stand, gait speed — these are the predictors of what your seventies look like, and they are all downstream of muscle.
What actually protects lean mass
Three things, and the first is non-negotiable.
1. Progressive resistance training, 2 to 3 times per week.
This is the intervention with the strongest evidence for preserving lean mass during weight loss. Not walking. Not Pilates. Progressive loading of the major movement patterns — squat, hinge, push, pull, carry — with load that increases over time.
Resistance training during caloric restriction has been shown repeatedly to preserve substantially more lean mass than caloric restriction alone. This is one of the most reliable findings in exercise science.
2. Protein intake, deliberately prioritised.
This is a genuine challenge on GLP-1 medications, because they work partly by reducing appetite. Total intake falls, and protein — the most satiating macronutrient — is often the first thing displaced.
The evidence in older adults supports intakes around 1.2 to 1.6 g of protein per kilogram of bodyweight per day for preserving muscle, higher than the standard RDI. During active weight loss, the requirement is at the upper end of that range.
Distributing protein across meals, rather than concentrating it at dinner, appears to improve the muscle protein synthesis response in older adults. Discuss specific targets with your GP or an Accredited Practising Dietitian — particularly if you have kidney disease.
3. Monitoring, so you know what is happening.
Weight on a scale tells you nothing about composition. Two people can lose 15 kg with completely different outcomes.
Worth tracking through the process:
- Grip strength — the fastest, cheapest whole-body strength proxy
- 30-second sit-to-stand — lower limb strength and power
- Gait speed
- DXA body composition, if accessible, at baseline and follow-up
- Strength in the gym — if your working loads are climbing while your weight falls, you are winning
The framing we’d suggest
If you are on a GLP-1 medication, or considering one, the useful question is not whether to take it. It is: what am I doing to make sure the weight I lose is fat?
The medication controls the appetite side of the equation. Resistance training and protein control the composition side. Doing only the first produces a smaller, weaker version of you. Doing both produces the outcome you were actually after.
This article is general information, not medical advice. Decisions about medication are between you and your prescribing doctor.
Book an assessment
At Longevity Physio Studio in Eagle Heights, Mt Tamborine, we work with people on weight loss medication to build and monitor the strength side of the equation — with baseline measurements so you can see what is actually happening to your body.
Serving Tamborine Mountain, North Tamborine, Canungra and the Gold Coast hinterland. Book an assessment.