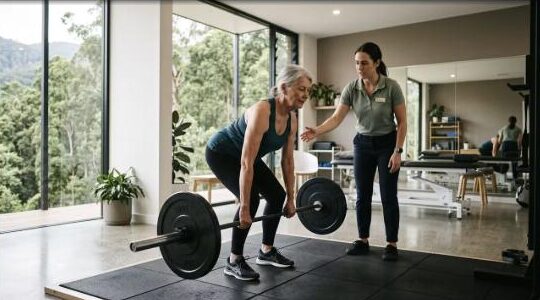Here is a statistic that ought to be better known than it is.
Roughly one in four to one in three people over 65 who sustain a hip fracture are dead within twelve months. Not from the fracture. The bone heals. The surgery is generally excellent. Australian orthopaedic care for hip fracture is, by global standards, very good.
They die from what the fracture starts.
The cascade
A hip fracture — also called a broken hip, femoral neck fracture, neck of femur fracture, proximal femur fracture, intertrochanteric fracture, or fractured NOF — sets off a chain that has very little to do with bone.
Day 0 to 2: Surgery, anaesthesia, opioids. Delirium occurs in a substantial proportion of older patients and independently predicts worse outcomes.
Day 2 to 10: Bed rest. This is the expensive part. Older adults on strict bed rest can lose meaningful quadriceps muscle mass within a week. Muscle protein synthesis in older adults is already blunted; immobilisation makes it worse.
Week 2 to 8: Reduced weight-bearing, reduced walking, reduced appetite. Sarcopenia accelerates. Bone density drops further with disuse.
Month 3 to 12: Fear of falling. Reduced activity. Social withdrawal. A person who walked 6,000 steps a day now walks 900. Cardiorespiratory fitness falls off a cliff. Pneumonia, cardiac events, and a second fall become far more likely.
Many people never return to their pre-fracture level of function. A significant proportion who lived independently before the fracture do not live independently a year later.
The fracture is not the disease. The fracture is the moment the pre-existing disease became visible.
The pre-existing disease
Here is the part that matters for anyone reading this before a hip fracture.
The people who do badly after a broken hip are, overwhelmingly, the people who arrived at the fracture with low muscle mass, low strength, low aerobic fitness and poor balance. They had no reserve. Ten days of bed rest took them below the threshold for independent function and they never climbed back.
The people who do well are the ones with reserve. Same fracture. Same surgery. Different trajectory — entirely because of what was in the tank beforehand.
This is why the single most valuable thing a physio can do about hip fracture is not rehab. It is prehab.
What reserve actually looks like
You can measure it, which means you can build it.
- Grip strength — a proxy for whole-body strength and a strong predictor of post-surgical outcomes
- 30-second sit-to-stand — lower limb power and a strong functional marker
- Gait speed — under 0.8 m/s is a warning sign
- Single-leg stance — the fall risk itself
- Calf and quadriceps capacity — the muscles that fail first with bed rest
- Bone mineral density — the fracture threshold
Most Australians over 65 have never had any of these measured. Most have had their cholesterol measured a dozen times.
The two-front strategy
Reducing hip fracture risk means acting on two fronts simultaneously, and doing only one is the common mistake.
Front one: don’t fall. Balance training, reactive stepping, ankle and hip strength, vision, medication review, vestibular screening, home hazards.
Front two: be robust if you do. Bone mineral density through progressive heavy resistance training and impact loading. Muscle mass and strength so that ten days in bed doesn’t take you below threshold. Aerobic fitness so you tolerate surgery.
Front two is the one that gets neglected, and it is the one that determines the twelve-month outcome.
“Isn’t heavy lifting dangerous for osteoporosis?”
This is the objection we hear most often at our Eagle Heights clinic, and the research says otherwise. Supervised high-intensity resistance and impact training in older adults with low bone mass has been studied specifically — most notably in Australian research out of Griffith University — and has been shown to improve bone density and function with a strong safety record when properly supervised.
The genuinely dangerous option is doing nothing and arriving at 80 with no reserve.
Book a prehab assessment
If you are over 60, if you have osteopenia or osteoporosis, if you have had a fall in the last year, or if a parent had a hip fracture, the window to build reserve is now.
Longevity Physio Studio in Eagle Heights, Mt Tamborine, works with people across Tamborine Mountain, North Tamborine, Canungra and the Scenic Rim on exactly this problem.
Book an assessment. We will measure your reserve and tell you honestly where you stand.