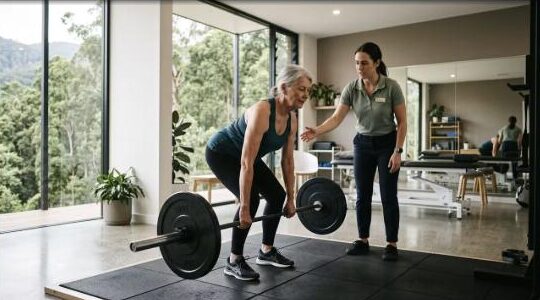Hip osteoarthritis is usually described to patients as a countdown. The joint is wearing out; the replacement is inevitable; the only question is when.
That framing is wrong in an important way, and the way it is wrong costs people years of good function.
Hip osteoarthritis — also known as hip arthritis, hip OA, coxarthrosis, degenerative hip disease, wear and tear hip, or simply “a worn hip” — is a condition of the whole joint system: cartilage, bone, synovium, capsule, and critically, the muscles that control it. Only one of those is genuinely irreversible.
Where hip arthritis actually hurts
A quick diagnostic aside, because this catches people out constantly.
Hip osteoarthritis usually presents as groin pain, often with a deep ache into the front of the thigh, sometimes referring to the knee. It stiffens with rest and eases with gentle movement. Internal rotation is typically the first range lost — putting on socks and getting out of a car become telling.
Pain on the outside of the hip is usually not hip osteoarthritis. That is far more often gluteal tendinopathy, greater trochanteric pain syndrome, or trochanteric bursitis. Pain in the buttock radiating down the leg is more likely lumbar or deep gluteal in origin.
People are frequently treated for one when they have the other. An accurate physio assessment sorts this out in about fifteen minutes.
The three deficits that drive the symptoms
When we assess hip osteoarthritis at Longevity Physio Studio in Eagle Heights, three findings turn up almost every time.
Gluteal weakness. Gluteus medius and minimus stabilise the pelvis in single-leg stance. When they fail, the pelvis drops, the joint is loaded asymmetrically, and gait develops the characteristic lurch. This is measurable and highly trainable.
Loss of hip extension. Sitting for decades shortens hip flexors and reduces extension range. Without hip extension, the low back compensates, which is why hip arthritis and back pain travel together.
Reduced load tolerance. The joint has become deconditioned to load — not because the cartilage cannot handle it, but because the muscular envelope around it can’t.
All three respond to progressive strength training. None of them respond to rest.
What the evidence supports
Clinical guidelines internationally, including Australian guidelines, place education and exercise as first-line management for hip osteoarthritis, ahead of medication and well ahead of surgery.
The GLA:D program, delivered in clinics across Australia, has registry data showing meaningful improvements in hip pain and function, with a substantial share of participants deferring or reconsidering joint replacement.
Importantly, exercise does not appear to accelerate joint degeneration. The mechanical intuition — that loading a worn joint wears it faster — is not supported. Cartilage and subchondral bone are metabolically active tissues that respond to appropriate load.
The “buy a decade” strategy
Here is the practical framing we use on Tamborine Mountain.
A hip replacement is a very good operation with a finite lifespan — commonly quoted as roughly 15 to 25 years, depending on the implant, the patient, and their activity. If you have a replacement at 55, revision surgery is a realistic prospect. Revision is a bigger operation with poorer outcomes.
If you can maintain good function to 70 with strength and load management, you likely get one hip that lasts you the rest of your life.
That is the deal on offer: build the muscular envelope, keep the range, keep walking, and push the surgery later.
What “building it” actually means
Not clams on a mat. Not a resistance band around the knees.
Genuine strength work: loaded hip hinge patterns, split squats, step-ups, leg press, hip abduction with meaningful resistance, and progressive walking or cycling volume. Two to three sessions per week, progressed over months.
Pain during and after strength work is expected to some degree and does not indicate damage. We teach a monitoring framework so you know when to progress and when to hold.
We also address the aerobic side, because hip arthritis is a leading cause of activity reduction in the over-60s, and reduced activity is the mechanism by which a joint problem becomes a longevity problem.
And if you do need the replacement
Then the strength work becomes prehab. Preoperative strength and function are among the strongest predictors of postoperative outcome. Patients who go into a hip replacement strong get out of hospital faster, walk further sooner, and return to normal life earlier.
There is no scenario in which building your hip strength is wasted effort.
Book a hip assessment
If you have groin pain, stiffness getting out of the car, difficulty with socks and shoes, or you have been told you will need a hip replacement “eventually,” it is worth finding out exactly what is driving it.
Longevity Physio Studio is in Eagle Heights, Mt Tamborine, serving Tamborine Mountain, North Tamborine, Canungra and the Gold Coast hinterland. Book an assessment.