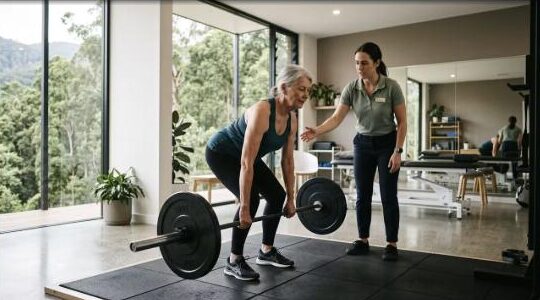The shoulder is where the “rest it” instinct does the most damage.
Rotator cuff tendinopathy — variously called shoulder impingement, subacromial pain syndrome, supraspinatus tendinitis, rotator cuff tendinitis, subacromial bursitis, shoulder bursitis, or a partial-thickness cuff tear — is the most common cause of shoulder pain in adults over 50.
And the standard advice sequence is: rest it, take anti-inflammatories, have a cortisone injection, and if that doesn’t work, have surgery.
There is now good evidence that this sequence gets it close to backwards.
The surgery finding
In 2018, the CSAW trial was published in The Lancet. It compared arthroscopic subacromial decompression surgery against a placebo arthroscopy — patients were taken to theatre and had the camera inserted, but nothing was decompressed — and against no treatment.
The real surgery was not meaningfully better than the placebo surgery.
That result, replicated in other trials, forced a substantial rethink. If shaving bone off the acromion is no better than pretending to, then “impingement” was probably never the mechanism.
What is actually going on
The current understanding is far less mechanical and far more useful.
A tendon is a living tissue that adapts to load. Tendinopathy develops when the load applied exceeds the tendon’s current capacity — either because the load went up (you painted the ceiling, you started swimming, you took up golf again) or because the capacity went down (you got older, you stopped using the shoulder overhead, you had a period of illness).
The tendon becomes painful and its capacity drops further. Then it hurts to use, so you use it less, so capacity drops further still. The spiral is the disease.
Notably, structural findings on imaging are a poor guide. Partial-thickness rotator cuff tears are extremely common in pain-free shoulders over 60. Finding one on your ultrasound does not establish it as the source of your pain.
Why rest is the wrong lever
Rest lowers the load. It does not raise the capacity. So it feels better while you’re resting and hurts again the moment you resume — because the capacity gap is unchanged or worse.
Cortisone works on the same principle. It is very effective at reducing pain in the short term, which is genuinely valuable when pain is severe. But it does nothing for capacity, and there is evidence that repeated injections may have negative effects on tendon tissue. It is a window, not a treatment.
What loading looks like
A rotator cuff loading program in a physio clinic is not three sets of theraband external rotations forever.
It progresses:
Phase 1 — isometrics. Sustained holds, often at moderate to high intensity, in a comfortable range. These frequently produce immediate short-term pain relief and allow loading when movement is provocative.
Phase 2 — heavy slow resistance. Loaded external rotation, internal rotation, and scapular work, progressed to genuine loads. Tendons respond to magnitude of load, not repetition count.
Phase 3 — range and function. Restoring overhead capacity. Loaded overhead pressing is the goal for most people, not a movement to be permanently avoided.
Phase 4 — capacity for the actual task. Whether that is gardening on a Tamborine Mountain slope, swimming, hanging washing, or lifting grandchildren.
Alongside this, we address the whole chain: thoracic mobility, scapular control, lower trapezius and serratus anterior capacity, and neck contribution. A shoulder that cannot get its scapula to rotate upward will keep loading the cuff badly no matter how strong the cuff gets.
Age is not the obstacle people think
Tendons in older adults do change — they become stiffer, collagen turnover slows, and the response to load takes longer. But they still respond. The adaptation window is longer, not closed.
Which means the instruction “you’re 68, you have to expect some shoulder trouble” is not a diagnosis. It’s a shrug.
Why this belongs on a longevity site
Upper body strength is one of the most neglected areas of ageing. Grip strength gets discussed. Pushing and overhead capacity almost never do — and they determine whether you can get yourself up off the floor, break a fall with your arms, lift a suitcase into an overhead locker, or push yourself out of a chair.
A shoulder that hurts overhead means a person who stops loading their upper body entirely. Over ten years, that is a large amount of lost muscle and bone.
Book a shoulder assessment
If you have shoulder pain reaching overhead, pain lying on that side at night, pain reaching behind your back, or you have been told you have impingement, bursitis or a cuff tear, an accurate assessment will tell you what your shoulder can currently tolerate and how to build from there.
Longevity Physio Studio, Eagle Heights, Mt Tamborine — serving Tamborine Mountain, North Tamborine, Canungra and the Gold Coast hinterland. Book an assessment.