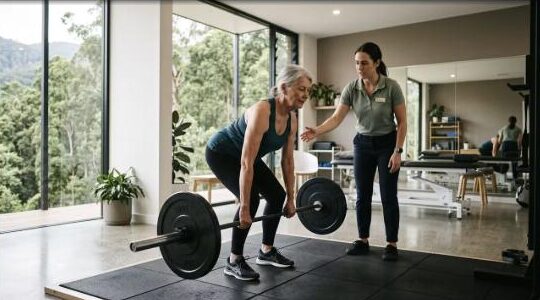In every yoga class there is someone who can fold in half with no apparent effort, put their palms flat on the floor with locked knees, and bend their thumb to their forearm. Everyone else is quietly envious.
That person is, statistically, more likely to be in a physiotherapy clinic within five years than anyone else in the room.
The names
Hypermobility goes by several labels: joint hypermobility, generalised joint hypermobility, being double jointed, benign joint hypermobility syndrome (an older term), hypermobility spectrum disorder, and — at the more significant end — hypermobile Ehlers-Danlos syndrome (hEDS).
Estimates vary considerably by population and criteria, but generalised joint hypermobility is common — more so in women, in younger people, and in some ethnic groups. The majority of hypermobile people have no problems at all.
The question is not whether you are flexible. It is whether you are flexible and weak.
The Beighton score
The standard screening tool, out of nine points:
- Little finger bends past 90 degrees (one point each side)
- Thumb touches the forearm (one point each side)
- Elbow hyperextends past 10 degrees (one point each side)
- Knee hyperextends past 10 degrees (one point each side)
- Palms flat on floor with knees straight (one point)
Thresholds vary with age and sex, but a score of 5 or more in adults generally indicates generalised joint hypermobility. It is a screen, not a diagnosis, and it does not capture every hypermobile joint.
Why extra range is a liability without strength
Joints rely on two stabilising systems. Passive stability comes from ligaments, capsule and bony architecture. Active stability comes from muscle. In a hypermobile person, the passive system contributes less. Which means the active system has to contribute more — and if it doesn’t, the joint operates at the end of its available range with nothing holding it.
Proprioception is often reduced. Joint position sense relies partly on receptors in ligaments and capsule. When those structures are more compliant, the signal is degraded. Hypermobile individuals frequently have poorer joint position sense, which means they reach dangerous positions without noticing.
End range becomes the default. A hypermobile person standing at rest tends to hang on their ligaments — hyperextended knees, anteriorly tilted pelvis, hyperextended elbows. Passive tissue is loaded continuously.
Recovery is slower. Connective tissue differences can mean healing and adaptation take longer.
The typical presentation: recurrent ankle sprains, shoulder subluxations, patellofemoral pain, jaw problems, low back pain, and diffuse fatigue.
Why yoga and Pilates are the wrong first prescription
This is uncomfortable but important.
A hypermobile person with pain seeks something gentle. They are told stretching and mobility work will help. They go to yoga.
Yoga rewards exactly what they are already too good at. They find the poses easy, they push into deeper ranges because they can, and they load their passive tissues further. They feel wonderful for an hour and their symptoms are unchanged or worse over months.
The same applies to routine massage, foam rolling, and end-range mobility work. They are all addressing a deficit the person does not have.
What hypermobile people need is the opposite: strength, control, and time under tension in the middle of the range.
What actually works
Progressive resistance training. Heavy, controlled, and — this is the key modification — deliberately avoiding end range initially. Squats stopping short of full depth. Presses stopping short of elbow lockout. Building the active stabilisers.
Isometrics. Sustained holds build joint position sense and strength without ballistic loading.
Proprioceptive training. Balance and joint position work, progressed deliberately.
Postural re-education. Learning to stand and sit out of end range. This is genuinely difficult, because end range feels like rest to a hypermobile person.
Load management and pacing. Particularly where fatigue is a feature.
Progression is slower than in a non-hypermobile person, and consistency matters more. But the outcomes are good — hypermobile people respond well to strength training when it is prescribed correctly.
The longevity view
A hypermobile 30-year-old who never builds strength becomes a 60-year-old with widespread joint pain, early osteoarthritis in several joints, poor balance, and a long history of “unlucky” injuries.
A hypermobile 30-year-old who trains strength consistently becomes a 60-year-old with excellent range of motion and the muscle to control it — which is genuinely an advantage.
The flexibility is not the problem. The unaccompanied flexibility is.
Book an assessment
If you have always been bendy, and you have collected more sprains, dislocations and unexplained aches than seems reasonable, an assessment will tell you where the control is missing.
Longevity Physio Studio, Eagle Heights, Mt Tamborine — serving Tamborine Mountain, North Tamborine, Canungra and the Gold Coast hinterland. Book an assessment.