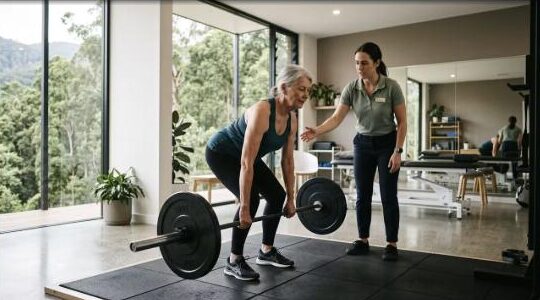A woman turns 49. Over about eighteen months, the following happens.
Her shoulder starts hurting and gradually freezes. Her hands ache in the morning. Her Achilles becomes sore for the first time in her life. Her hip develops a nagging pain on the outside that makes lying on that side impossible. She feels weaker. Her recovery from exercise takes days rather than a day.
She sees a GP about the shoulder. Then a different practitioner about the hip. Then someone about the hands. Each problem is treated as a separate, unlucky event. Somewhere in there, someone says “well, we’re all getting older.”
They are not separate events. They are one event with several addresses.
The syndrome
In 2024, Vonda Wright and colleagues published a paper in Menopause proposing that this cluster be recognised as the musculoskeletal syndrome of menopause.
The components:
- Arthralgia — joint pain, affecting a majority of women through the menopause transition
- Loss of muscle mass and strength — accelerated sarcopenia
- Loss of bone density — the sharpest rate of bone loss in a woman’s life occurs in the years around the final menstrual period
- Tendinopathy — Achilles, gluteal, rotator cuff, elbow
- Adhesive capsulitis — frozen shoulder, which peaks precisely in this age window
- Progression of osteoarthritis
Estimates of joint pain prevalence during the menopause transition commonly land around 70% of women. Yet it remains one of the least-discussed symptoms, well behind hot flushes and sleep disturbance.
Why oestrogen
Oestrogen is not solely a reproductive hormone. Oestrogen receptors are expressed in muscle, tendon, ligament, cartilage, bone, and synovium.
When oestrogen falls:
Bone. Osteoclast activity increases relative to osteoblast activity. Bone resorption outpaces formation. Women can lose a substantial share of bone mineral density in the years surrounding menopause.
Muscle. Oestrogen influences muscle protein synthesis, satellite cell function, and repair after loading. Its decline is associated with reduced muscle mass and impaired recovery.
Tendon and connective tissue. Oestrogen affects collagen synthesis and tendon mechanical properties. Changes in tendon stiffness and repair capacity plausibly underlie the tendinopathy cluster.
Cartilage and synovium. Receptors are present; the mechanism for arthralgia is less well characterised but the epidemiological pattern is clear.
This is an area of active research and the causal picture is still being filled in. But the pattern is not in dispute, and the practical implications are not either.
Why “it’s just ageing” is the wrong answer
Because ageing is gradual and this is not. This is a step change compressed into a few years, and it arrives at exactly the moment when the decisions a woman makes about training determine the next four decades.
Consider the arithmetic. Bone density peaks around 30 and declines slowly. Then menopause accelerates that loss sharply. If a woman enters menopause with low bone density and low muscle mass, and responds to the joint pain by exercising less, she is compounding the problem during the single most consequential window available to her.
If she instead enters that window strong, and keeps loading through it, the trajectory looks entirely different.
What actually helps
Progressive resistance training. This is the highest-value intervention and it is not optional. It addresses muscle mass, bone density, tendon capacity, joint pain and metabolic health simultaneously. It needs to be genuinely progressive — heavy enough to drive adaptation, not a set of light dumbbells.
Impact and high-velocity loading. Bone responds to rapid, high-magnitude load. Australian research from Griffith University has shown supervised high-intensity resistance and impact training can improve bone density in postmenopausal women with low bone mass.
Protein. Requirements rise with age and with reduced anabolic sensitivity. Most women in this group are eating well under what the evidence supports.
Tendon-specific loading. Tendinopathies in this window respond to progressive loading, but often need longer and more patient programs than the same condition in a 35-year-old.
Medical management. Menopausal hormone therapy and its role in musculoskeletal symptoms is a conversation for your GP or a menopause specialist. It sits outside physiotherapy scope, but it is a legitimate part of the picture and worth raising.
Book an assessment
If you are in your late forties or fifties and you have collected two or three musculoskeletal problems in the last couple of years, they are probably not a coincidence.
At Longevity Physio Studio in Eagle Heights, Mt Tamborine, an assessment includes strength testing, grip strength, functional capacity measures, review of bone health and DEXA if available, and a look at every one of the symptomatic areas as parts of one picture rather than separate complaints.
Serving Tamborine Mountain, North Tamborine, Canungra and the Gold Coast hinterland. Book an assessment.